Silent for 75 years: a case report of a congenital factor VII deficiency revealed by a haemorrhage in the brainstem
Salma Jerbi, Fatma Medhioub, Dorsaf Dalensi, Wiem Feki, Zina Hakim, Farah Zouari, Rania Allela
Corresponding author: Salma Jerbi, Intensive Care Unit, Regional Hospital of Mahres, Faculty of Medicine of Sfax, University of Sfax, Sfax, Tunisia 
Received: 14 Oct 2025 - Accepted: 09 Apr 2026 - Published: 22 Jul 2026
Domain: Intensive care medicine,Internal medicine
Keywords: Factor VII deficiency, intracranial haemorrhages, aged, congenital disorders
Funding: This work received no specific grant from any funding agency in the public, commercial, or non-profit sectors.
©Salma Jerbi et al. PAMJ Clinical Medicine (ISSN: 2707-2797). This is an Open Access article distributed under the terms of the Creative Commons Attribution International 4.0 License (https://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited.
Cite this article: Salma Jerbi et al. Silent for 75 years: a case report of a congenital factor VII deficiency revealed by a haemorrhage in the brainstem. PAMJ Clinical Medicine. 2026;21:21. [doi: 10.11604/pamj-cm.2026.21.21.49771]
Available online at: https://www.clinical-medicine.panafrican-med-journal.com//content/article/21/21/full
Case report 

Silent for 75 years: a case report of a congenital factor VII deficiency revealed by a haemorrhage in the brainstem
Silent for 75 years: a case report of a congenital factor VII deficiency revealed by a haemorrhage in the brainstem
 Salma Jerbi1,&, Fatma Medhioub1, Dorsaf Dalensi1, Wiem Feki2, Zina Hakim3, Farah Zouari1, Rania Allela1
&Corresponding author
Congenital factor VII deficiency is a rare autosomal recessive disorder typically diagnosed in childhood due to bleeding symptoms. Here, we describe a remarkable case of a late diagnosis in a 75-year-old woman. A 75-year-old woman with no prior bleeding history who presented with coma. Neuroimaging revealed spontaneous haemorrhaging in the mesencephalon. Laboratory evaluation showed a significant and isolated prolongation of prothrombin time, recorded at less than 10%, with no response to plasma transfusion. Further hematologic evaluation identified a specific deficiency of factor VII. The absence of factors supporting an acquired deficiency indicates this condition is congenital. This rare presentation of congenital factor VII deficiency at an advanced age supports the idea that inherited coagulopathies should be considered in cases of spontaneously occurring intracerebral haemorrhages, even in the elderly population.

Factor VII (FVII) is involved in initiating the coagulation cascade via the extrinsic pathway. Congenital deficiency is extremely rare (1 in 500,000) and usually recognised in early life, particularly in those with symptoms. Acquired deficiencies are more common in the older adult population and typically result from liver disease, vitamin K deficiency, and/or the use of anticoagulants. We present an atypical case of a woman diagnosed with congenital FVII deficiency who was 75 at the time of diagnosis and revealed by a spontaneous brainstem (mesencephalic) haemorrhage. Of note is the complete absence of any previous bleeding episodes or surgical intervention complications, which underscores the unpredictable expressivity of this condition.

Patient information: a 75-year-old woman was found unresponsive at home. Her medical history included type 2 diabetes mellitus, hypertension, primary hypothyroidism (on levothyroxine), adrenal insufficiency (on hydrocortisone), and dyslipidemia. She had no prior history of abnormal bleeding, excessive bruising, or anticoagulant use.
Clinical findings: on arrival, she was deeply comatose (GCS 3) with miotic pupils and respiratory distress (oxygen saturation 60% on room air). Blood pressure was 110/80 mmHg, and heart rate was 80 bpm. Capillary blood glucose was 0.5 g/L, confirming severe hypoglycemia. Despite immediate intravenous glucose administration, her neurological status did not improve, and she required endotracheal intubation for airway protection.
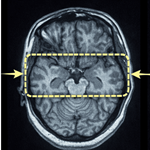
Timeline: after stabilisation and ICU admission, the patient was diagnosed with hypoglycemic coma complicated by aspiration pneumonia. Laboratory evaluation showed a markedly prolonged prothrombin time (<10%) and INR >2.5, with normal APTT, platelet count, and liver and renal function tests. That’s why she received fresh frozen plasma (FFP) transfusions without improvement in PT or INR. A brain CT scan was initially normal, but a subsequent MRI revealed hyperintense lesions in the cerebral peduncles and left inferior colliculus, with a gradient-echo signal void consistent with mesencephalic haemorrhage and diffuse cortical and basal ganglia changes characteristic of hypoglycemic encephalopathy.
Diagnostic assessment: inflammatory markers were elevated (CRP 170 mg/L, leukocytes 31,370/mm3) and consistent with infection. Specific coagulation testing revealed Factor VII activity of 8%, with normal levels of other clotting factors (V, VIII, IX, X, XI). Vitamin K levels were normal, and autoimmune markers (ANA, antiphospholipid antibodies, and rheumatoid factor) were negative. A mixing study corrected the PT from 26% to 75%, excluding the presence of inhibitors. In the absence of liver disease, vitamin K deficiency, or anticoagulant exposure, a diagnosis of congenital Factor VII deficiency was established.
Therapeutic intervention: the patient was treated with recombinant activated factor VII (rFVIIa, NovoSeven®) at a dose of 30 µg/kg once weekly. Supportive management included mechanical ventilation, intravenous antibiotics for aspiration pneumonia, glycemic stabilisation, and hemodynamic support.
Follow-up and outcomes: despite appropriate replacement and supportive therapy, the patient remained comatose. Her condition was complicated by septic shock, leading to death after one month of ICU hospitalisation.
Patient perspective: on the management and outcome.
Informed consent: as the patient was deceased and written informed consent from the next of kin could not be obtained despite reasonable efforts, publication of this fully anonymised case report was approved by the Institutional Ethics Committee based on its significant scientific and educational value and in accordance with applicable ethical standards. For transparency, the Institutional Ethics Committee's approval letter has been provided as part of the submission.
Inherited factor VII deficiency is the most common of the rare autosomal recessive bleeding disorders. Coagulation factor VII (FVII) is a vitamin K-dependent serine protease produced in the liver that is found in plasma. Factor VII is also the only coagulation factor that has a small free circulating percentage of its active form (FVIIa) (1-3%) despite the lack of coagulation activation [1].
While the serious forms have a relatively high incidence of recurrent hemarthrosis (19%) and gastrointestinal bleeding (15%), central nervous system bleeding is rarer (2.5%); however, it can be the most serious and life-threatening bleeding symptom. Severe bleeding occurs soon after birth or in infants, and the bleeding phenotypes follow the same distinct pattern of onset. Specifically, umbilical stump bleeds carry a significant risk of developing further severe bleeds (CNS and GI) at a young age. An intracranial haemorrhage (ICH) may be the presenting symptom in a newborn or infant. Bleeding after circumcision or heel stick in the neonatal period and dental extractions as a child are common and expected in hereditary Factor VII deficiency [2,3]. While it is very rare in the literature for a late-onset presentation in adulthood, where spontaneous ICH is the first symptom, as in our case, it does occasionally happen.
A multi-centre study of congenital factor VII (FVII) deficiency with centralised genotyping and specific functional assays was conducted in 59 centres across Europe, Asia, Australia, New Zealand and the Americas in 2005. FVII mutations described in patients (n=313) were highly heterogeneous (103 different, 22 novel). Clinical phenotypes were notably variable from asymptomatic presentations to severely disabled patients suffering life-threatening CNS, GI bleeding, and hemarthrosis, strongly associated with a young age of presentation (median age 7.2) and included population were all of the age of <40 years old. [3]. In addition, Wang et al. conducted a single study in 2022 with 26 patients, published in the Pediatric Haematology Oncology Journal. The median age of the first bleed was 7 days [4].
Lastly, Tripathi et al. conducted an 18-month retrospective observational study of possible inherited factor VII deficiency. The study group consisted of a total of 12 cases of factor VII deficiency. The mean age of the study group was 28 years (range 4-68 years), and the median age of onset of bleeding symptoms was 17.5 years (range 2-47 years). Only one of the patients seen, a 68-year-old, was identified as part of routine blood work [5]. Notably, another case was published of a 57-year-old male of Northern Italian and Polish descent with a mild andlate-onset hereditary factor VII deficiency who sustained bilateral intracranial subdural hematomas after performing "sit-ups" in a head-down position on an inversion table [6]. Also, a case report published by Ip HL et al. in the Journal of Stroke and Cerebrovascular Diseases involved a man diagnosed with factor VII deficiency at age 70 years old, who presented with an acute cerebrovascular accident [7].
In our patient, the ICH was the first manifestation of the previously undiscovered FVII deficiency. The haemorrhage progressed, the clinical course deteriorated, and the patient succumbed to septic shock despite adequate treatment and administration of recombinant activated factor VII (rFVIIa).
This case emphasises the importance of continuing to evaluate congenital bleeding disorders, even in elderly patients presenting with acute, unexplained hemorrhagic events. Isolated severe PT prolongation that does not respond to plasma transfusion should prompt a hematologic assessment. Clinicians should stay vigilant for rare diagnoses and uncommon clinical presentations when traditional management fails.
The authors declare no competing interests.
All the authors read and approved the final version of this manuscript.
- Napolitano M, Siragusa S, Mariani G. Factor VII Deficiency: Clinical Phenotype, Genotype and Therapy. J Clin Med. 2017 Mar 28;6(4):38. PubMed | Google Scholar
- Di Minno MN, Dolce A, Mariani G; STER Study Group. Bleeding symptoms at disease presentation and prediction of ensuing bleeding in inherited FVII deficiency. Thromb Haemost. 2013 Jun;109(6):1051-9. PubMed | Google Scholar
- Mariani G, Herrmann F, Dolce A, Batorova A, Etro D, Peyvandi F et al. International Factor VII Deficiency Study Group. Clinical phenotypes and factor VII genotype in congenital factor VII deficiency. Thromb Haemost. 2005 Mar;93(3):481-7. PubMed | Google Scholar
- Wang A, Su D, Chen Y, Fu Y, Tan X, Luo J et al. Phenotypic and genotypic characterization of two factor VII deficiency patients from southeastern China. Blood Coagul Fibrinolysis. 2022 Dec 1;33(8):468-472. PubMed | Google Scholar
- Tripathi P, Mishra P, Ranjan R, Tyagi S, Seth T, Saxena R. Factor VII deficiency - an enigma; clinicohematological profile in 12 cases. Hematology. 2019 Dec;24(1):97-102. PubMed | Google Scholar
- Barton JC, Bertoli LF, O'Malley S. Bilateral subdural hematomas in an adult with hereditary factor VII deficiency: A complication of sit-ups and inversion? Clin Appl Thromb Hemost. 2009 Mar-Apr;15(2):242-4. PubMed | Google Scholar
- Ip HL, Chan AY, Ng KC, Soo YO, Wong LK. Case report: a 70-year-old man with undiagnosed factor VII deficiency presented with acute ischemic stroke. J Stroke Cerebrovasc Dis. 2013 Nov;22(8):e664-6. PubMed | Google Scholar
Search

This article authors
On Pubmed
On Google Scholar
Citation [Download]
Navigate this article
Similar articles in
Key words
Article metrics
Recently from the PAMJ-CM